Key Takeaways
- Tinnitus is the perception of sound that has no external source, most often described as ringing, buzzing, hissing, or a high-pitched tone.
- Statistics Canada's analysis found that about 37 percent of Canadian adults, roughly 9.2 million people, had experienced tinnitus in the past year, and that it was bothersome for 7 percent.
- The most common route into tinnitus is damage to the hair cells of the inner ear from noise exposure, aging, or the two combined.
- Tinnitus and hearing loss travel together frequently but not inevitably, and one in five Canadian adults has tinnitus with no measured hearing loss at all.
- There is no cure for tinnitus, and there is a considerable amount of effective treatment, which are two very different statements.
Tinnitus is the perception of sound without any external source producing it, most often ringing, buzzing, or hissing that only you can hear. It is far more common than most people assume when they first notice it.
If you have been lying awake listening to a ringing that nobody else in the room can hear, you are in the company of several million other Canadians. This article from Toronto Hearing Consultants explains what is generating that sound, why it behaves the way it does, and what an audiologist can realistically do about it.
What Tinnitus Actually Is
The sound you are hearing is real, and it is being generated inside your own auditory system rather than in the room around you. Most tinnitus is subjective tinnitus, which means that only you can hear it. It takes the form of ringing, buzzing, hissing, roaring, or a steady high-pitched tone sitting somewhere behind ordinary sound. A much smaller group has pulsatile tinnitus, which pulses in time with the heartbeat.
Pulsatile tinnitus originates in blood flow near the ear rather than in the hearing pathway itself. That distinction matters clinically, because it warrants medical assessment in a way that ordinary ringing usually does not.
The scale of it in Canada is striking. Statistics Canada's analysis of the Canadian Health Measures Survey covered 6,571 adults aged 19 to 79. It found that 37 percent of them had experienced tinnitus in the past year, and that 60 percent of Canadian adults had hearing loss, tinnitus, or both.
What Causes Tinnitus?
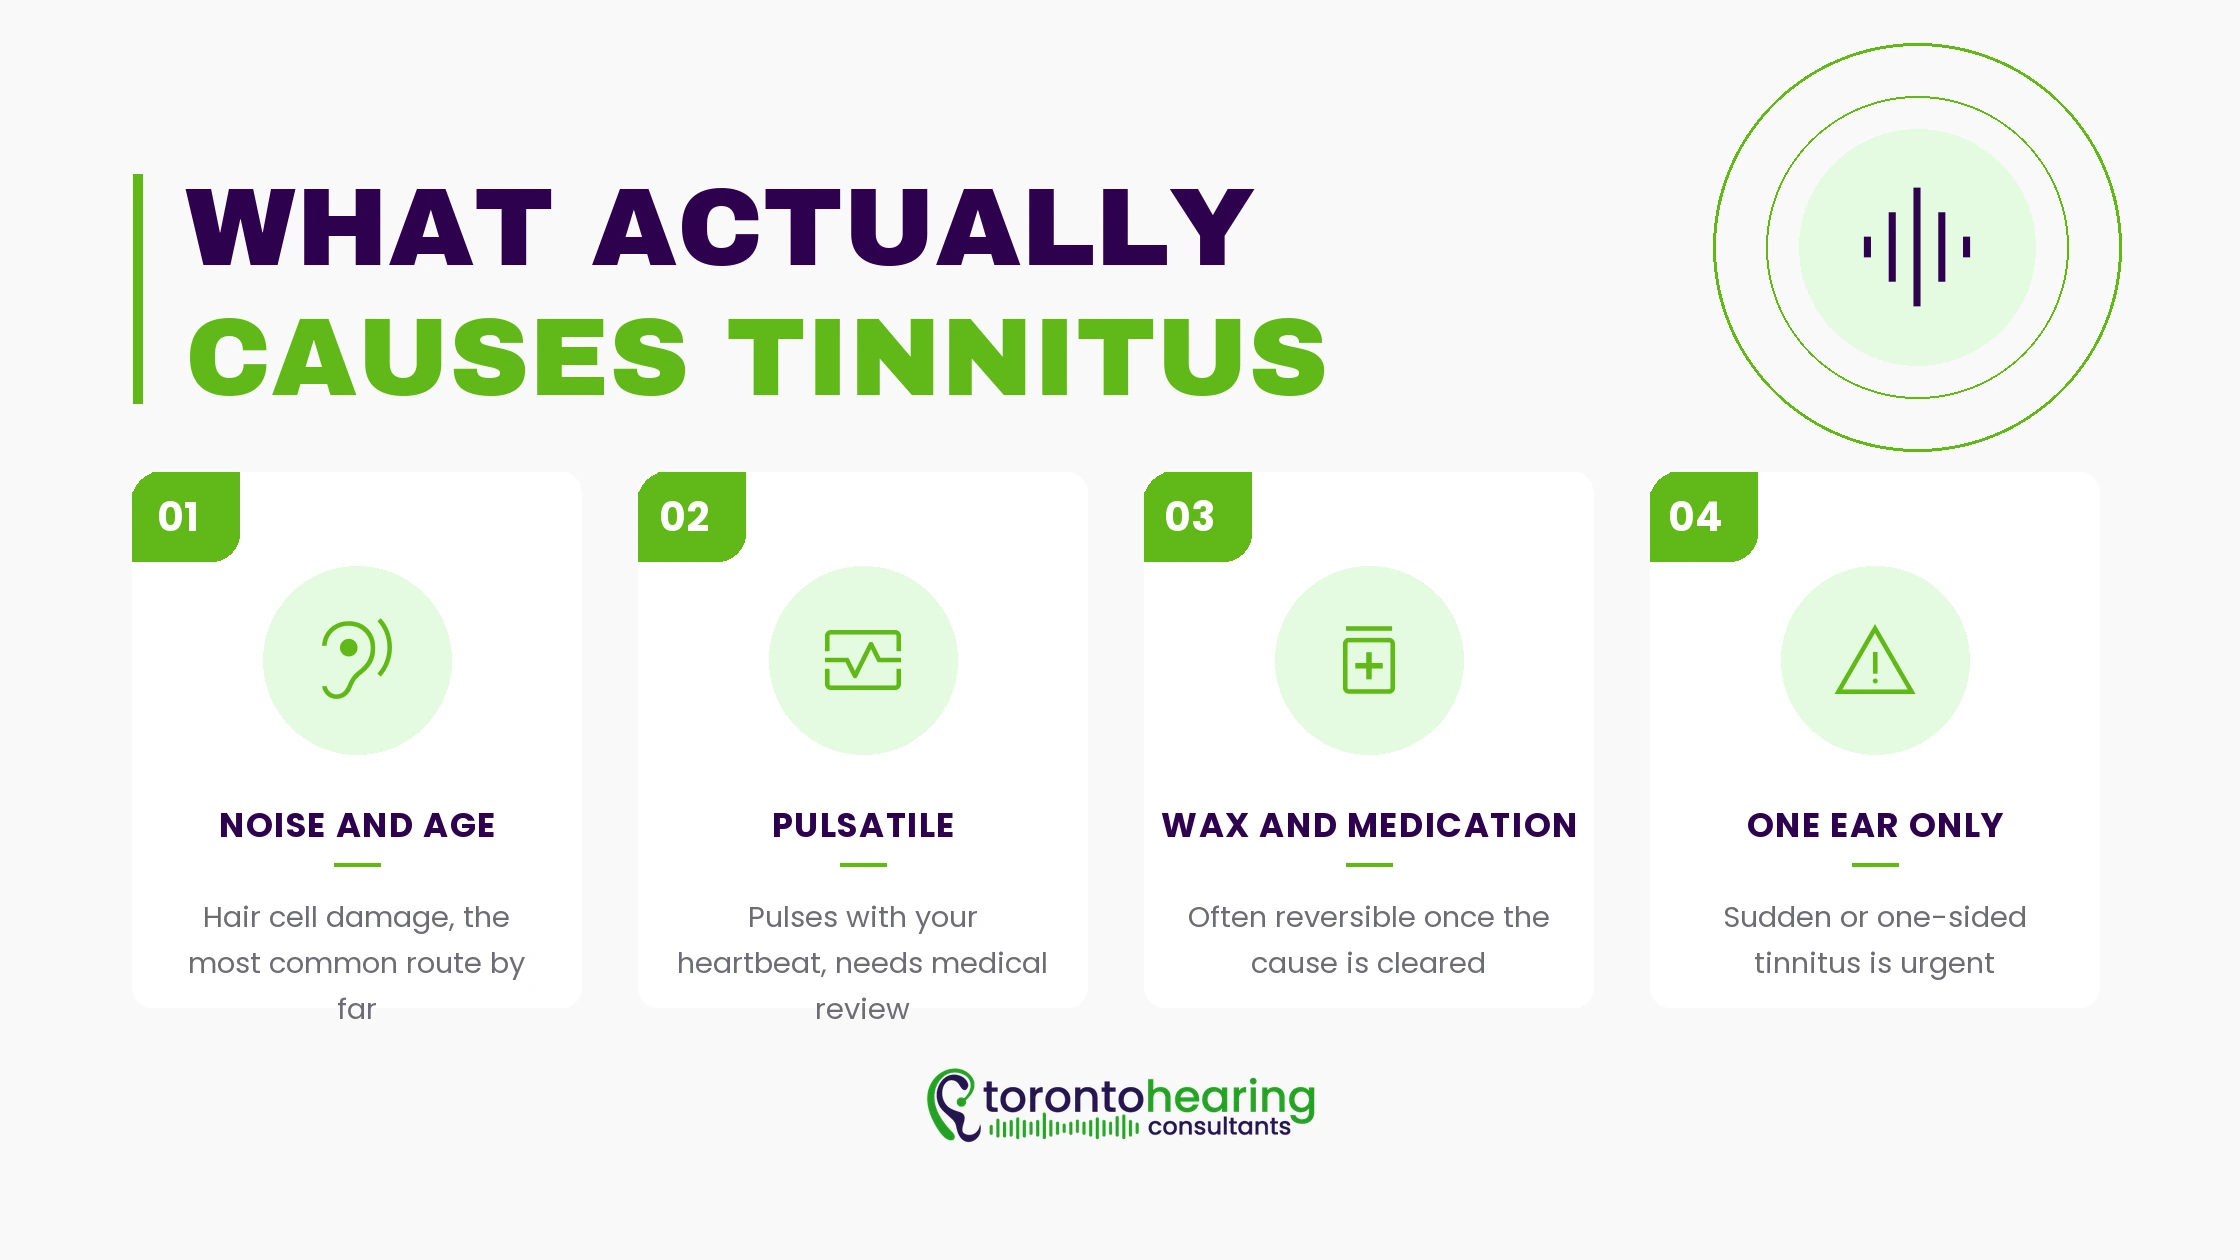
Most tinnitus begins in the cochlea, the fluid-filled spiral of the inner ear lined with delicate hair cells that convert vibration into nerve signals. Those hair cells do not regenerate once they are damaged, and the two things that damage them most reliably are loud noise and time.
Noise-induced hearing loss is the cause we see most often in people who worked in construction, manufacturing, music, or transportation. We now see it nearly as often in people whose exposure came from concerts and headphones rather than a job site.
Age-related change accounts for another large share, and the two overlap constantly in the same patient. Several other routes are worth knowing about:
- Impacted earwax, which blocks the ear canal and can produce ringing that resolves entirely once the blockage is professionally cleared
- Ototoxic medications, meaning drugs that can damage the inner ear, including some antibiotics, some chemotherapy agents, and high doses of acetylsalicylic acid
- Middle ear infection and other conditions that change how sound is conducted through the ear
- Meniere's disease, which combines fluctuating hearing loss, vertigo, and a sensation of fullness with tinnitus
- Head and neck injury, jaw joint problems, and certain cardiovascular conditions
Stress does not cause tinnitus on its own, though it reliably makes existing tinnitus louder and harder to ignore. That is why so many people first notice theirs during a difficult stretch at work.
Why Tinnitus and Hearing Loss Travel Together
The connection is real, and it is mechanical. When hair cells are damaged, the cochlea sends less signal up to the brain, and the auditory system responds by turning up its own sensitivity to compensate for the missing input.
Auerbach, Rodrigues, and Salvi described this in Frontiers in Neurology as central gain enhancement, defining it as the compensatory increase in central auditory activity in response to the loss of sensory input. The trouble is that this amplification does not distinguish between real sound and the auditory system's own background activity.
Think of that neurological shift like a stereo receiver hunting for a weak radio station. When the signal from the ear drops, the brain automatically turns up its own internal volume to compensate, and what it amplifies is not just the station. The frustrating result is that everyday quiet moments fill with sound that was always there and was never audible before.
That model explains the pairing, and it does not explain every case, because the Statistics Canada's analysis data is clear that the two conditions are not locked together. Twenty-two percent of Canadian adults had tinnitus with no measured hearing loss, which works out to roughly one in five. Anyone who has been told their tinnitus cannot be real because their hearing test looked fine has been given information that the national data does not support.
Why Tinnitus Gets Worse at Night
This is the question we hear more than any other, and the answer follows directly from the central gain mechanism above. During the day, your auditory system is busy with traffic, conversation, appliances, and the general hum of a city.
All of that sound sits at a level that covers your tinnitus without you ever noticing it happening. At night, that competing sound disappears; your auditory system has almost nothing external to work with, and the compensatory amplification climbs.
Your attention also turns inward once you stop moving, so a sound you successfully ignored all afternoon becomes the most interesting thing in the room. The practical consequence is encouraging, because a problem created by silence can be addressed with sound. A fan, a quiet radio, or a sound machine reduces the contrast between your tinnitus and the room. Most people find that the ringing recedes considerably once the auditory system has something else to attend to.
When Tinnitus Needs an Audiologist
Tinnitus that has been stable for years and does not bother you needs monitoring rather than intervention. Several patterns, however, warrant a proper assessment rather than patience.
Book an appointment if your tinnitus is in one ear only, if it appeared suddenly, if it pulses in time with your heartbeat, or if it arrives alongside dizziness, ear pain, or a noticeable change in hearing. Sudden hearing loss with tinnitus is treated as urgent in audiology, because the window for effective medical treatment is measured in days rather than weeks.
You should also be assessed if the tinnitus is affecting your sleep, your concentration, or your mood. Statistics Canada's analysis found tinnitus associated with poor self-reported mental health, high daily stress, and poor quality sleep, and those effects are treatable even where the tinnitus itself cannot be switched off.
A diagnostic tinnitus assessment does more than measure what you can hear. Your audiologist also runs pitch and loudness matching, playing tones until you identify the one that sounds like your tinnitus and the level at which it sits. That gives your tinnitus a number instead of a mystery, establishes a baseline to measure any change against, and tells us directly which sound therapy settings are likely to mask it.
What Treatment Actually Looks Like
Woods and Theodoroff put the position plainly in Audiology Today, writing that there is no cure for tinnitus, and that no cure is not equivalent to no treatment. That sentence is worth carrying with you, because the gap between those two ideas is where every useful intervention lives.
Assessment comes first, and a full diagnostic hearing test establishes whether hearing loss is present, whether it is one-sided, and whether anything needs medical referral. Where earwax turns out to be the culprit, clearing it can resolve the ringing on its own, which is the simplest good outcome available.
Where hearing loss accompanies the tinnitus, well-fitted hearing aids in Toronto frequently help twice over. They restore the input the auditory system was missing, which reduces the compensatory amplification driving the tinnitus, and they bring back environmental sound that partially covers whatever ringing remains.
Modern devices do considerably more than amplify speech. Most current hearing aids carry built-in sound therapy generators that your audiologist can tune to your own tinnitus, and that you can then adjust yourself through a smartphone app. That matters in practice, because it gives you ongoing control in the situations that actually bother you, whether that is a busy social gathering, an open-plan office, or a silent bedroom at two in the morning.
Sound therapy uses controlled background sound to reduce the contrast between tinnitus and silence, either through dedicated devices or through those built-in generators. Tinnitus retraining therapy combines that sound enrichment with structured counselling, teaching the brain to classify the tinnitus as unimportant so that it stops commanding attention.
Cognitive behavioural therapy has the strongest evidence base of any tinnitus intervention, and it is recognised as such across audiology practice in Canada and internationally. It is usually delivered by psychologists and counsellors over six to ten sessions, and it works on the distress and the attention rather than on the volume.
Prevention deserves a mention here too, since the hair cells you still have are worth protecting. Custom earplugs fitted to your own ear canals are the practical answer for musicians, tradespeople, and anyone who spends time around loud sound.

What Does Not Work
Supplements marketed as tinnitus cures are the most common disappointment we hear about, and no dietary supplement has been shown to eliminate tinnitus in good-quality research. If a product promises to make your tinnitus disappear, the promise itself is the warning sign.
Waiting it out is the other common mistake, particularly where hearing loss is present and progressing. The advice to simply learn to live with it is outdated, and it tends to leave people managing something on their own that has established management pathways.
Find Out What Is Generating Your Tinnitus
Toronto Hearing Consultants provides audiologist-led tinnitus support at both our Bloor West Village and Annex clinics, serving patients across the broader Greater Toronto Area. We are independent, which means the recommendation follows your assessment results rather than a product line, and we will tell you plainly when sound therapy is likely to help and when it is not.
The assessment is $50 for patients over 50, $90 for patients under 50, and $110 for children, and private insurance plans commonly reimburse it. Audiology diagnostics are not covered by OHIP, so you do not need a referral, and there is no waiting list. If you are not sure which path is right for you, contact us to arrange a complimentary 15-minute consultation and we will point you to the right starting place.
Frequently Asked Questions
What Is the Most Common Cause of Tinnitus?
Damage to the hair cells of the inner ear is the most common cause, usually from noise exposure, aging, or the two combined. Those cells convert vibration into nerve signals and they do not regenerate once lost, so tinnitus arising this way is typically permanent. Permanent is not the same as untreatable. Most people who seek help find the sound becomes far less intrusive with sound therapy, hearing aids where loss is present, and structured counselling aimed at the distress rather than the volume.
Can Tinnitus Go Away on Its Own?
Tinnitus from a temporary cause often resolves once that cause is addressed, and impacted earwax, a middle ear infection, or a single loud event are the usual candidates. Tinnitus tied to permanent hair cell damage generally persists, although the brain frequently learns to attend to it far less over months and years. That habituation is real and it can be accelerated deliberately. Waiting to see what happens is the one approach we would discourage, particularly where hearing loss is also present.
Why Is My Tinnitus Worse at Night?
Daytime background sound partially covers tinnitus without you ever noticing the covering happening. When that sound disappears at night your auditory system increases its own sensitivity to compensate for the quiet, and your attention turns inward once you stop moving. The result is a sound you ignored all afternoon becoming the loudest thing in the room. Adding low-level sound to the bedroom, whether a fan, a quiet radio or a sound machine, reduces the contrast and usually helps considerably.
Does Tinnitus Mean I Am Going Deaf?
Not necessarily, and the Canadian data is reassuring on this point. Statistics Canada's analysis found that roughly one in five Canadian adults has tinnitus with no measured hearing loss at all, so the two conditions travel together often without being locked together. It is still worth having your hearing tested, because tinnitus is an early signal that something has changed, and a baseline audiogram is useful either way. Tinnitus in one ear only, or arriving suddenly, warrants prompt assessment rather than monitoring.
Can Hearing Aids Help Tinnitus?
They often help when hearing loss is present, and they work on the problem from two directions at once. Restoring the input your auditory system has been missing reduces the compensatory amplification that drives the tinnitus, and bringing back environmental sound partially covers whatever ringing remains. Many current hearing aids also include built-in sound generators you can adjust from a smartphone app. Where hearing is normal, amplification is not the answer and we will say so rather than fitting devices you do not need.